


Mobile wound care Fayetteville GA patients arrange sounds like a convenience, and it is one. No drive, no parking lot, no waiting room with a dressed foot propped on a bag. All of that is real, and none of it is the clinical reason a home visit works.
The reason is duller and more useful. A wound gets professional attention for an hour or so a week. The remaining time it spends in a house, under conditions nobody on the care team has ever laid eyes on. A good many wounds that stall are being held open by something in that house. When the appointment happens in a consulting room, every one of those conditions has to arrive second-hand, described from memory by somebody who was never told which details count.
This page covers what a visiting clinician is actually looking at, what a visit involves, how the record differs, how clinic, home and telehealth care fit together, how to judge any provider offering this, and what decides what you pay.
On this page
- What a home visit is actually for
- Six things a consulting room never sees
- What mobile wound care Fayetteville GA visits cover
- The record a home visit produces
- Clinic, home or telehealth
- Fayetteville, Atlanta and the rest of Georgia
- How to judge any provider offering this
- What decides what you pay
- What to avoid
- Living with a service that comes to you
- When to call before the next visit
- Questions about home visits
- The half that cannot travel
What a home visit is actually for
It is not a clinic appointment that has been delivered to your door. It is a different examination, and the difference is what surrounds the wound.
Almost everything that decides whether a wound closes sits outside the wound itself. Pressure is a property of furniture. Whether a dressing lasts its interval depends on the surface it was applied on and the light somebody was working under. Whether the routine gets kept depends on who is in the house and whether they were ever taught anything. None of that is medical trivia. It is the treatment, and it is invisible from a chair fifteen miles away.
A clinic can ask about all of it, and does. The trouble is what happens to the answers. You describe your armchair accurately and leave out the seam you have stopped noticing. You say the dressing changes go fine, because they do, and never mention that you do them sitting on the edge of the bath because it is the only place you can reach. Nobody can report a detail they were never told was a detail. That gap is not carelessness on anybody’s part, and it does not close by asking better questions, because the useful questions only become obvious to somebody standing in the room.
Which is the honest case for a visiting service. You are not buying comfort. You are giving a clinician access to the other half of the problem.
Six things a consulting room never sees
These are ordinary and they come up constantly. None of them is a failing on the patient’s part, and every one of them changes a plan when somebody notices it.
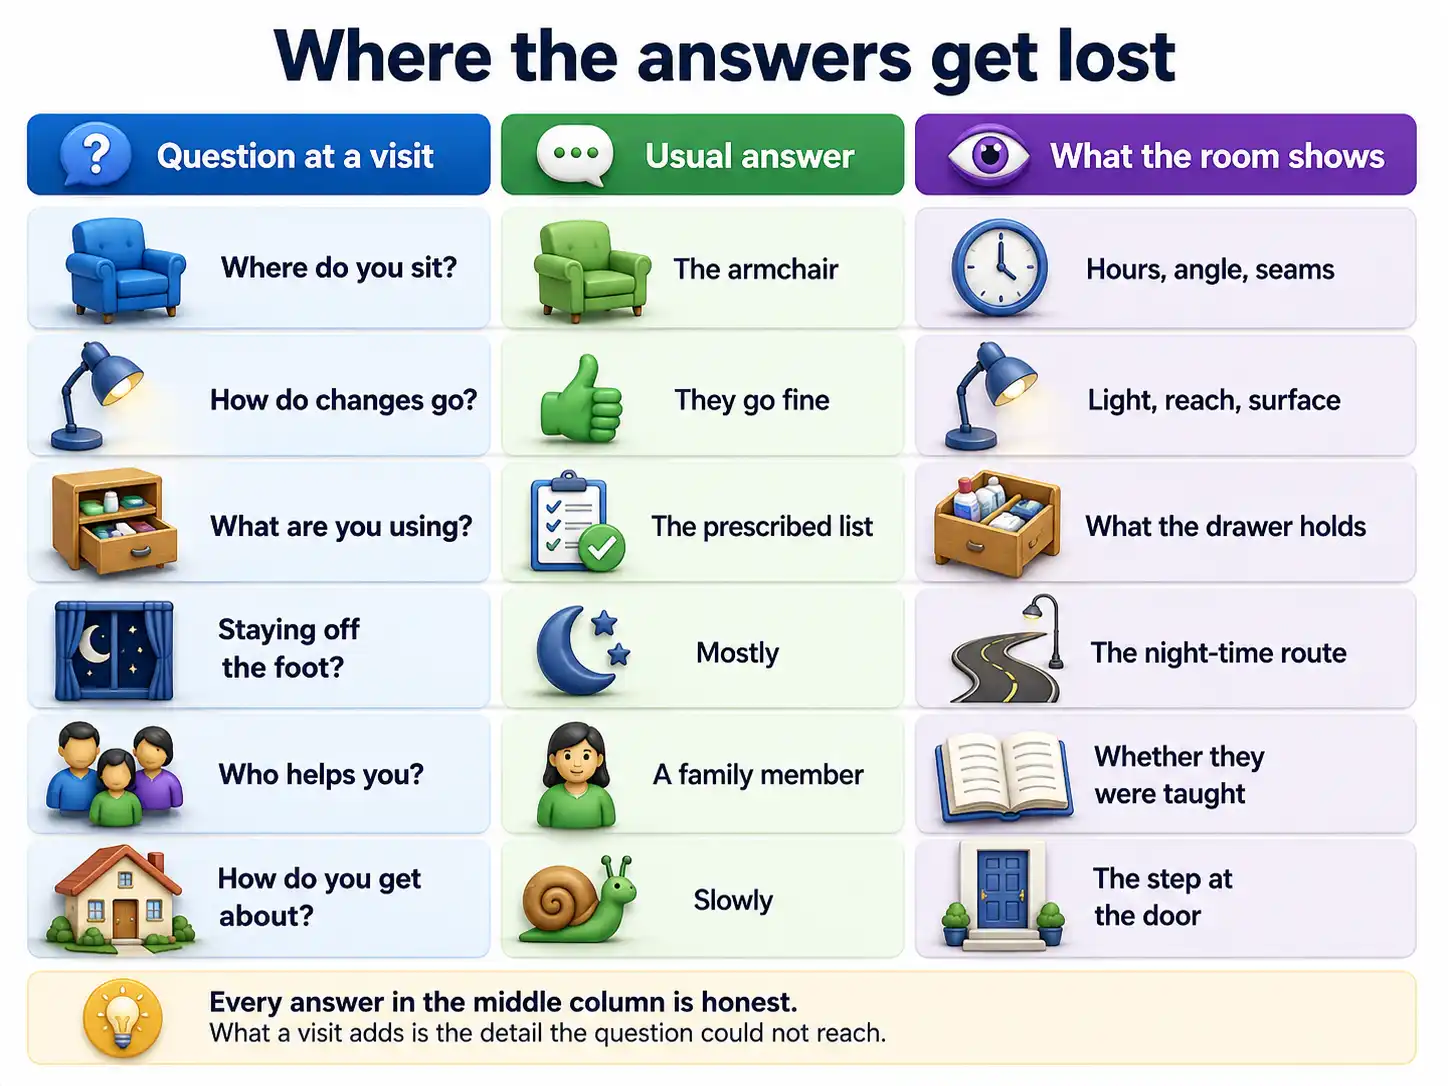
Where the weight lands. Somebody who spends fourteen hours a day in one chair has a pressure problem shaped by that chair, and the shape is not something anybody can describe. The seam, the angle of recline, the arm they lean on, the side they sleep on. Pressure injuries are caused by furniture and by time, and only one of those two is discussed at appointments.
Where the change happens. A dressing applied in poor light, at an awkward angle, by somebody who cannot quite see what they are doing, is a different dressing from the same product applied properly. So is one laid out on a surface that was not wiped. Watching a change once tells a clinician more about why dressings keep failing than a month of asking about it.
What is in the drawer. The prescribed list and the material actually going on the wound diverge more often than anybody admits, usually for practical reasons. A box ran out and something similar looking was substituted. An old product from a previous plan is still in the cupboard and gets used because it is there. An interval slipped because supplies did not arrive. Opening a drawer settles in ten seconds what a conversation rarely gets to.
The route to the bathroom. Anyone told to keep weight off a foot answers questions about walking by thinking about journeys, which means shopping, appointments and stairs. Almost nobody counts the trip taken at three in the morning, without the boot, across a cold floor. On a foot wound those unprotected steps matter, and they only surface when somebody has seen the distance involved. Offloading a diabetic foot ulcer covers the pressure side of that in full, including why the short indoor trips carry more weight than people expect.
Who is really doing this. The person named as the carer and the person doing the daily change are not always the same, and the second one is frequently somebody who has never been shown. Teaching them takes one visit. Discovering they exist takes being in the house.
How somebody moves unobserved. People walk differently down a corridor toward a clinician than they do around their own kitchen. The step down at the back door, the way somebody gets out of a low chair, the hand on the counter for balance. Those are findings, and they routinely explain a wound whose cause was previously listed as unclear.
What mobile wound care Fayetteville GA visits cover
The same assessment, done to the same standard, with a smaller set of equipment. The address does not lower the bar.
A visit generally covers examining and measuring the wound, describing the tissue in the base and the condition of the skin around it, cleaning, clearing dead material where that is needed, choosing and applying the dressing, judging whether infection is a live question, checking the circulation to the limb, and recording all of it against the previous reading. Advanced treatments including negative pressure therapy can be set up and managed at the bedside. Teaching whoever handles the wound between visits is part of the visit and not an extra.
What does not travel is a short list, and it pays to know it before assuming everything can be done at home. Anything needing a device molded to the foot, imaging, a procedure requiring an operating room, and some equipment that is simply too large to carry. Where a wound needs one of those, the visit is what establishes that it does. Diabetic foot ulcer treatment in Fayetteville GA takes up how that split works on a foot specifically, and why the journey to an appointment is itself part of the clinical problem there.
The part that gets least attention is what happens after the clinician leaves. Findings have to reach whoever else is treating you, because a wound plan that nobody else knows about is the commonest way for two sensible treatments to work against each other. Ask at the first visit where the notes go and how often they go there. A specific answer means the arrangement already exists. A vague one means the job is about to become yours without anybody saying so.
The record a home visit produces
People arrive at this subject wanting to see before and after pictures, which is understandable and points at the wrong thing.
What makes a series of wound readings mean anything is that they are comparable. The trouble with wound photographs is almost never the wound. It is everything else: a different room, a different lamp, a different angle, a different phone held at a different distance in a different week. Two pictures taken that way can disagree about a wound that has not changed at all, and they can agree about one that has.
A visiting service happens to hold most of those variables still. Same room, same chair, same window, frequently the same clinician with the same tape. When the only thing changing between one reading and the next is the wound, a run of measurements starts to carry real information, and a wound that is not moving becomes obvious weeks earlier than it otherwise would.
That is the honest version of results, and it tells you more than any gallery, because the only comparison that tells you anything about your wound is the one made against your own earlier readings. Somebody else’s photographs describe somebody else’s circulation, somebody else’s glucose and somebody else’s wound. Wound care covered by Medicare Part B works through why published patient galleries are not something a clinic should be offering in the first place.
The practical consequence for you is small and takes one sentence. Ask what the wound measured at the last two visits. If the numbers are available and moving in the right direction, that is the answer. If they are not available, that is a different and more important answer.
Clinic, home or telehealth
Framing this as a choice between competing options is the standard mistake. Care is delivered three ways here, they are not ranked against one another, and most people end up on a mixture that shifts as the wound does.
Clinic visits exist for the things that need a room: instruments, a treatment chair, a device shaped to a limb. Mobile and in-home visits carry the bulk of ongoing treatment, and everything on this page is the argument for why. Telehealth is credentialed in every state we serve, and it is the one people undervalue. It does not replace an examination and should never be used to declare a wound fine on the strength of a video call. What it is good at is closing the gap between visits, at the point where something has changed and the next appointment is a week away.
The useful question is therefore not which one is best. It is which parts of your particular plan need a room, and whether anybody has actually asked that. For most people the honest answer is a smaller number of parts than they assumed.
Fayetteville, Atlanta and the rest of Georgia
A visiting service is bounded by driving time and not by where a building happens to stand, which is why the map for this looks nothing like the map for a clinic.
Fayetteville and Fayette County, the southern side of the metro area, Atlanta, and the smaller towns well beyond it are all inside the same arrangement, served through in-home visits and telehealth. The people this reaches best are the ones a clinic reaches worst. Where the nearest hospital wound center is most of a morning’s travel away, an open leg or foot wound is the very thing that makes the journey hardest, and missed appointments start accumulating in a file that afterward reads as non-compliance.
The clinician who arrives is ours: we do not work through partner clinics, so the record stays a single record. You will find the practice listed as The Wound Clinic, and its address is 1581 Carol Sue Ave Suite C, Terrytown, LA 70056, with 888-391-4999 handling scheduling and general questions alike. If you specifically want somewhere in Georgia to attend in person, put that question on the number before planning around an answer.
How to judge any provider offering this
Put these to anybody who visits wounds at home, including us. A provider who has thought about the work answers them in specifics, and one who has not will answer in adjectives.
Will it be the same clinician? This matters more here than almost anywhere, because the value of a visit accumulates. Somebody who saw the chair last month notices when it has been moved. A rotating list of visitors resets that to zero every time. Complete continuity is rarely promised by anyone honest, so what you are listening for is whether there is a small named team or an open roster.
What happens between visits, and on a Saturday? Wounds change on days nobody is scheduled. Ask who picks up the phone outside normal hours, what they can do when they do, and how quickly a visit can be brought forward. This is the question that most reliably separates a service from an agency.
Who gets written to? Ask which of your other clinicians receives the findings and on what schedule, and whether anybody would tell your prescriber if the wound changed direction.
What is the training behind the visit? Wound care is a specialty and the qualifications in it are real. It is entirely reasonable to ask what the visiting clinician’s background in wounds is, and what they lean on where a wound sits on skin that will not show redness clearly. Wound care for dark skin covers why that second question is the sharper of the two and what a good answer sounds like.
What is actually included? Ask whether measurement and documentation happen at every visit, whether teaching a family member is part of the service, whether supplies come with the visit or are ordered separately, and what happens if the wound needs something that has to be done in a clinic.
One more, and it is the one people leave out because it sounds rude. Ask what the provider does when a wound is not improving. Every wound service has stalled wounds. What distinguishes them is whether there is a point at which somebody reassesses instead of continuing.
What decides what you pay
Nobody can put a figure on a web page, and any figure you find on one is guesswork. What can be explained is where the number comes from.
For a visiting service the question that actually decides it is how your particular plan classifies a home visit, which is a fact about your coverage and not about your wound. Some plans treat it as an ordinary specialist visit. Some route it through a home health benefit with its own conditions attached. Some require authorization before the first visit instead of after it. Those are three different answers and only one of them applies to you.
So the productive move is a phone call to the number on your insurance card, not to a clinic, asking three things: whether a referral is needed, whether wound care at home requires prior authorization, and what your share is once the deductible has been met. Ten minutes spent there removes most of what people later find distressing about a bill.
Wound care covered by Medicare Part B explains how that structure behaves for anyone on Medicare, and Medicare Part B wound care in Georgia looks at the same question from the Georgia end. Plan contracts and billing for home visits are both things our team can go through with you by phone.
People also make a second comparison badly. Weighing a home visit against a clinic visit on price alone leaves out everything the clinic visit costs that never appears on a bill. Fuel and parking. The half day somebody takes off work to drive you. A taxi, if there is no driver. The day itself, which for many people is genuinely a whole day. None of those reaches an invoice, so they get treated as free, and they are not. Only you can add up that second column, and it is the one that decides which arrangement you can actually keep to.
What to avoid
Do not stage the house for the visit. This is the most common and the most self-defeating thing people do, and it is done out of pride, not carelessness. The good chair gets used instead of the usual one. The commode gets moved. The drawer of half-used supplies gets tidied away before anybody arrives. Every one of those removes a finding. The room is being examined alongside the wound, and a room arranged for company is not the room the wound lives in.
Do not save your questions for some future clinic appointment. The clinician standing in your kitchen can answer nearly all of them and is holding your notes.
Do not let somebody take over the dressing changes without having been taught in person, however capable they are and however clear the instructions look. Watching a change and doing one under supervision are different things, and the second is what a visit is for.
Do not assume that a professional who has been in the house would have mentioned anything that mattered. A visit is one hour on one day. Changes announce themselves on the other days, in front of the only person who is there.
And do not quietly drop a plan you cannot keep to. A routine the household cannot sustain is going to fail whatever the notes record about it, and the only version anybody can redesign is the one you have described honestly.
Living with a service that comes to you
Here is the part nobody warns you about, and it is not a reason to avoid this. It is a reason to know what you are agreeing to.
Being treated at home means being seen at home. People clean for two days before a visit, apologize for the carpet, and feel judged about a house they are managing while also managing a wound and quite often several other conditions. That anxiety is close to universal, and putting it down early helps, because a clinician who visits wounds for a living has been in a great many houses and is looking at a chair, a light and a drawer. The state of the place is not the subject.
There is a privacy cost too, and it is real. A car outside on a regular schedule is visible to neighbors. A wound that was previously a private matter becomes something the whole household knows about, and for some people that is the harder half of the arrangement.
Set against that is something people rarely expect. In a clinic you spend the appointment performing a version of yourself that is coping, because that is what waiting rooms do to people. At home you are not performing anything, and the person who does the daily changes finally gets to ask their questions in the room where they do them, with the actual supplies in their hand. That conversation is more useful than the one in the consulting room, and it is not available anywhere else.
The practical irritation is scheduling. A visit usually arrives inside a window instead of at a time, so a day gets organized around waiting. Ask how wide the window is and whether anybody calls ahead. It is a small thing that makes a large difference over months, and most services can accommodate it if asked.
When to call before the next visit
Having a clinician come to the house creates one specific difficulty, and naming it matters because it costs people days. Once somebody professional has looked at the wound and the room, it becomes very easy to assume that anything important would already have been caught. A visit is one hour on one day, and every finding below arrives on the other days, in front of you. None of it waits comfortably for the next scheduled appointment.
Call the same day for redness reaching skin that was clear when the clinician was last there, for fluid coming through a dressing well before the change was due, for pain that has started interrupting sleep when it was not doing that at the last visit, for an odor you notice without going near the dressing, for swelling or heat in the limb that was not present when it was last examined, and for a fever, which belongs to none of the changes described on this page.
Go to an emergency department the same evening for skin that has turned black or dusky, for a limb that is cold to the hand when the other one is not, or for shivering that will not settle. Those are not matters for a phone message.
If you have diabetes or reduced sensation in your feet, the threshold drops and the reason is mechanical and not cautious: the signal that normally tells somebody to call is pain, and that signal may not arrive at all. Diabetic foot ulcer stages sets out how those wounds are graded and what a grade leaves out, and osteomyelitis in a foot ulcer takes up what happens when an infection reaches bone.
Questions about home visits
Is care at home the same standard as care in a clinic?
The assessment and the treatment principles do not change with the setting. What changes is the equipment available in the room, which is a smaller difference than most people assume. A visiting clinician carries what a wound examination and a dressing change require. Where something genuinely needs a clinic, the visit is how that gets identified.
Do I have to be housebound to get visits?
Not as a matter of clinical need. Plenty of people who can travel are better served at home, particularly where the instruction is to stay off a foot. It may however matter for coverage, since some insurance benefits attach conditions of that kind. That is a question for your plan and not for the wound, and settling it before the first visit saves trouble later.
What kinds of wounds are treated at home?
The ordinary range of long-running wounds, which in practice means diabetic foot ulcers, venous and arterial leg ulcers, pressure injuries, surgical wounds that have been slow to close or have opened, and traumatic wounds in people who heal slowly. What decides suitability is the wound and the person, not the category. Leg ulcer types separates the three patterns behind most long-running leg wounds, since treatment differs sharply between them.
How often would somebody come?
It depends on the wound, how much fluid it produces and what the dressing on it is designed to do, and the interval usually changes as the wound does. It is set at assessment instead of chosen in advance, and an interval that keeps being missed is a reason to change the plan instead of a reason to try harder.
Can visits happen in a nursing or assisted living facility?
A visit follows the patient, so where somebody lives in a care setting the visit can generally go there. What to establish early is how the findings reach the staff who handle the wound on the other days, because that handover is where this arrangement most often loses information.
What should I have ready for a first visit?
A complete list of your medications, your insurance details, whatever dressings and supplies you currently have in the house, and whoever helps you with the wound if there is somebody. Leave the supplies where they normally live instead of gathering them up. Where they are kept and what is actually in the pile are both useful, and both disappear once everything has been collected into a bag.
The half that cannot travel
A wound is one thing a clinician can examine anywhere. The chair it presses against, the light the dressing goes on under, the drawer the supplies come from and the person who does the work on the other six days are the rest of the problem, and none of them fits in a car.
That is the whole argument. The travel saved is real enough, and it is the least interesting thing about a home visit. What you are actually arranging is for somebody qualified to look at the conditions the wound is living in, which is where the answer sits in a good many wounds that have stopped improving. Ask what can be done where you are, ask who else will be told what they find, and ask what the wound measured last time.
Managing a wound in a room nobody has seen?
An assessment can establish what the wound needs, which parts of that have to happen in a clinic, and how much of the rest can reach you where you already are. Most of a plan can be delivered without the journey.
Seeing the place a wound is actually being managed changes what gets recommended, which is why the first visit our mobile and home health wound care service makes is as much a survey of the room as an examination of the wound. Our wound care management education work covers the teaching side of it, so the routine gets learned properly instead of demonstrated once and left.
This article is general education and does not replace a clinical assessment. Home visits, coverage and treatment choices all depend on an individual examination, and any spreading redness, new swelling, sudden increase in pain or fever affecting a wound should be assessed the same day.
